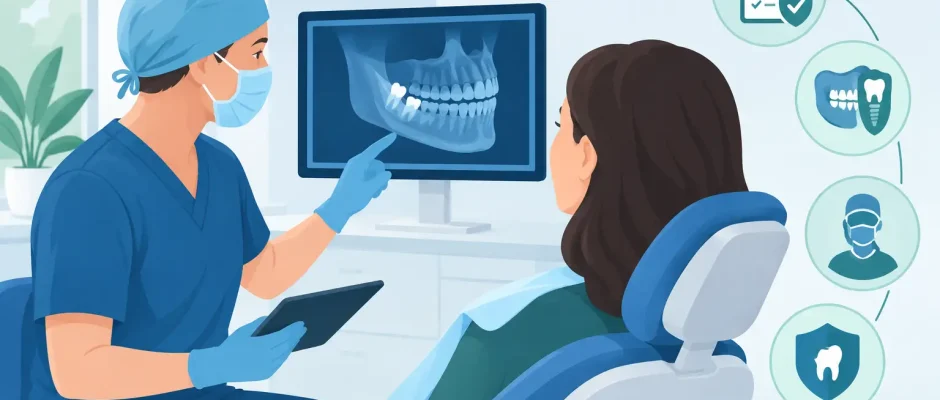
What a Safe Oral Surgery Plan Looks Like
A surgical recommendation should never begin with, “Let’s remove it” or “Let’s place an implant.” Oral surgery starts with a more useful question: what is causing the problem, what tissues must be protected, and which treatment plan gives the most stable result with the least unnecessary intervention?
For some patients, the answer is a straightforward extraction. For others, preserving a tooth with microsurgery is the better choice. When a tooth cannot be saved, implant placement may be possible on the day of extraction, or it may be safer to rebuild bone and allow healing first. The right approach depends on anatomy, infection, bone volume, gum condition, bite forces, and the patient’s overall health.
What Oral Surgery Includes
Oral surgery is not one procedure. It is a group of surgical treatments involving the teeth, jaws, bone, and surrounding soft tissues. The most common procedures include complex tooth extraction, removal of impacted wisdom teeth, dental implant placement, bone grafting, sinus lift procedures, and surgery to preserve a natural tooth.
A complex extraction may be necessary when a tooth is fractured below the gum line, severely decayed, tightly anchored in bone, or located close to important anatomical structures. Impacted or displaced wisdom teeth require particular attention because their roots may be near the mandibular nerve or the maxillary sinus.
Implant surgery is equally individualized. An implant is not simply placed where a missing tooth used to be. The surgeon evaluates whether there is enough bone in the correct three-dimensional position, whether the gum tissue can support a natural-looking result, and whether the final crown can be cleaned and loaded properly. A technically placed implant is not automatically a successful implant if the prosthetic plan and biology have not been considered first.
Diagnosis Comes Before the Procedure
The safest treatment often begins with deciding what not to do yet. A two-dimensional X-ray can be sufficient for some simple cases, but complex extractions, implant planning, bone augmentation, and sinus procedures often require three-dimensional imaging such as CBCT. This allows the surgeon to assess bone width and height, root anatomy, the position of nerves, sinus boundaries, and hidden infection.
A proper consultation also includes a review of medical history. Medications that affect blood clotting, diabetes control, smoking, osteoporosis treatment, previous radiation therapy, and immune conditions can change the surgical plan. These factors do not always prevent treatment, but they may affect timing, technique, antibiotic decisions, or the healing protocol.
Just as importantly, the final restoration should be planned before implant placement. If the goal is a single crown, a bridge, or a full-arch solution such as All-on-4, implant position must serve the future teeth. Placing an implant based only on available bone can create compromises in appearance, hygiene, or chewing function.
When a Tooth Should Be Saved
Extraction is sometimes necessary, but it should not be automatic. In selected cases, an infected tooth can be preserved through endodontic microsurgery, including root-end resection and sealing of the root tip. This may be appropriate when conventional root canal retreatment is not feasible or has already failed.
The decision depends on the remaining tooth structure, periodontal support, fracture risk, location of the infection, and long-term restorative prognosis. Saving a tooth with poor support can delay the inevitable. Removing a tooth that has a predictable chance of preservation can be equally premature. A responsible plan explains both options clearly.
Digital Planning Makes Surgery More Predictable
Digital tools do not replace surgical judgment, but they make that judgment more precise. CBCT data can be combined with digital scans to plan implant position in relation to the future crown, adjacent roots, nerves, and soft tissue. In suitable cases, a surgical guide transfers this plan to the clinical setting.
Guided surgery can improve accuracy, especially when anatomical space is limited or multiple implants are planned. It may also reduce surgical time and help make minimally invasive approaches possible. However, a guide is only as reliable as the diagnosis, digital design, and clinical execution behind it. It is a planning instrument, not a substitute for experience.
PRF, or platelet-rich fibrin, may also be used in selected cases. It is prepared from the patient’s own blood and can support soft-tissue healing and bone regeneration protocols. PRF is not a magic material and does not eliminate the need for sound surgical technique, stable grafting, or proper aftercare. Its value is in how it fits into a complete treatment protocol.
Bone Grafting and Sinus Lift Procedures
Bone loss after extraction is common, particularly when infection, trauma, or long-standing tooth loss is involved. If bone volume is insufficient for stable implant placement, guided bone regeneration may be recommended. This can involve grafting material, a protective membrane, and careful closure of the soft tissues.
In the upper back jaw, the maxillary sinus may limit available bone height. A sinus lift creates additional space beneath the sinus membrane so bone can form where an implant needs support. Depending on the amount of remaining bone and the stability achievable, the implant may be placed at the same appointment or in a later stage.
These procedures require patience. Immediate implant placement can shorten treatment in the right case, but it is not always the best choice. When infection is extensive, the socket walls are damaged, or implant stability would be inadequate, staged treatment often offers a more predictable foundation.
Comfort Is Part of Good Surgical Care
Fear of surgery is common, even among patients who have tolerated dental treatment before. Clear communication reduces much of that anxiety. Patients should know what will happen during the procedure, how long it is expected to take, what sensations are normal, and how pain and swelling will be managed afterward.
Local anesthesia is designed to make the surgical area numb. During treatment, patients may feel pressure or vibration, but they should not feel sharp pain. If discomfort occurs, it should be addressed immediately. For patients with significant anxiety or for more extensive procedures, additional sedation options may be discussed when appropriate.
Gentle tissue handling, microsurgical techniques, and precise suturing matter. They can reduce trauma and support cleaner healing, especially in visible areas or when gum contour is part of the final aesthetic result. Comfort is not separate from clinical quality. A controlled, well-planned procedure is usually easier for both the patient and the surgical team.
Recovery: What Is Normal and What Needs Attention
Recovery varies by procedure. A simple extraction may cause mild soreness for a few days, while bone grafting, impacted wisdom tooth removal, or full-arch implant treatment can require a longer healing period. Swelling often peaks around the second or third day and then gradually improves. Minor bruising, temporary stiffness, and small amounts of blood-tinged saliva may also occur.
After surgery, following instructions matters as much as the procedure itself. Patients are typically asked to protect the blood clot, avoid smoking, avoid vigorous rinsing early in healing, take prescribed medications exactly as directed, and maintain gentle oral hygiene around the surgical area. Food choices should match the procedure and the stage of healing.
Severe or increasing pain after initial improvement, persistent bleeding, fever, facial swelling that worsens after several days, difficulty swallowing or breathing, or numbness that does not improve should be assessed promptly. Complications are uncommon when planning and aftercare are appropriate, but they should never be ignored.
Questions Worth Asking Before You Agree to Surgery
A good consultation should leave you with more than a price and a procedure name. You should understand the diagnosis, the available alternatives, the proposed sequence of treatment, and the reason one approach is recommended over another.
Ask whether three-dimensional imaging is needed, whether the tooth has a realistic chance of being saved, whether grafting is likely, and what determines eligibility for immediate implant placement. If implants are planned, ask how their position will be coordinated with the final restoration. You should also know what follow-up visits are included and who to contact if recovery does not follow the expected course.
For patients traveling for treatment in Tel Aviv, scheduling deserves special attention. Surgical stages, healing checks, and the timing of the final restoration should be planned realistically rather than compressed around travel dates. A carefully organized sequence protects the result better than rushing a biological process.
The most reassuring next step is not a promise that surgery will be easy. It is a consultation that replaces uncertainty with a precise diagnosis, a transparent plan, and enough time to make an informed decision.


